
Dry eye · MGD
MGD eye drops: what helps meibomian gland dysfunction, and what drops can’t do
MGD means the oil glands in your eyelids have blocked. The right drop can stand in for the missing oil for a while. Here is which drops make sense, how to get the most from them, and why clearing the glands comes first.
By Sohail Khan, Optometrist and Director, who has dry eye himself · Checked by Abra Arshad, Optometrist and Clinical Director · Updated 13 October 2026 · 10 min read
For meibomian gland dysfunction (MGD), the drops that make most sense are the ones that put oil back on the tears: lipid emulsion drops, liposomal sprays and drops containing perfluorohexyloctane, which slows evaporation. Use them preservative-free, alongside warmth on the lids and lid cleaning twice a day. Drops ease the symptoms, but they don’t unblock the glands. If you still need them many times a day after a few weeks of good home care, the glands usually need clearing.
What MGD is, in plain English
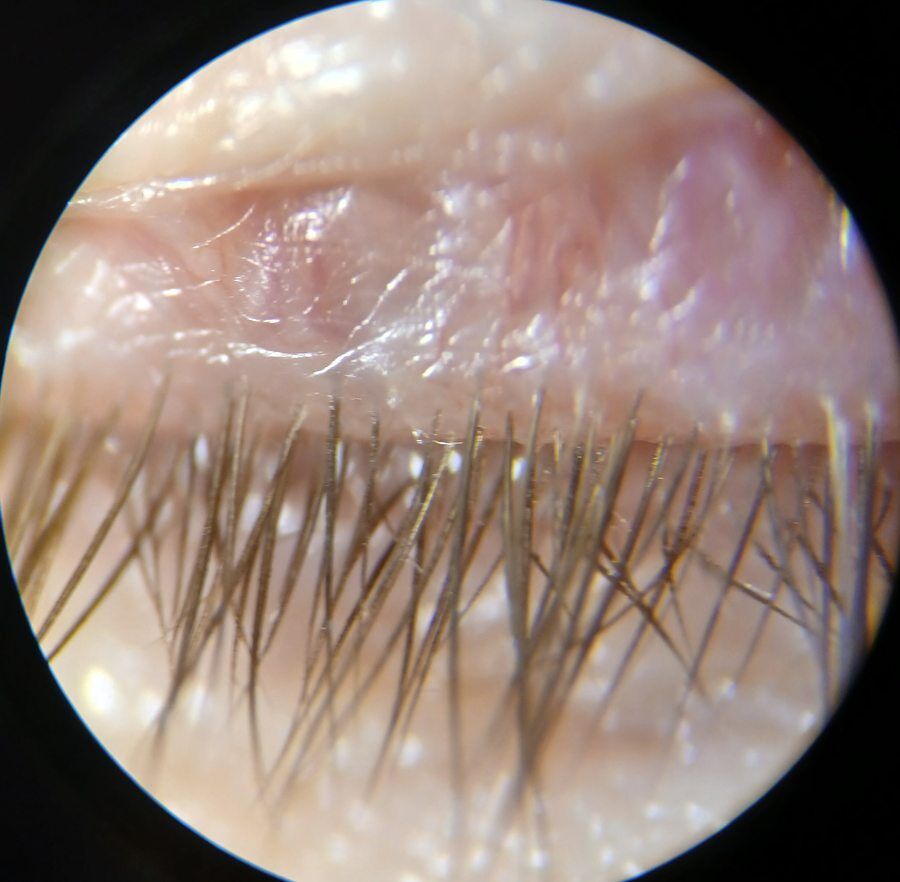
Along the edge of your eyelids are tiny oil glands, called meibomian glands: about 30 in the top lid and 25 in the bottom. They run from the lash line back into the lid like the teeth of a comb. Every time you blink, a little oil is squeezed out onto your tears, where it forms a thin film on top that stops the water evaporating.
Healthy oil is runny, a bit like olive oil. In MGD it thickens, more like butter, and sets inside the gland. The opening caps over, less oil reaches the tears, and the tears dry up in seconds. The eyes feel gritty, burn, look red at the lid edge and blur, then clear when you blink. Many people find their eyes water too, because a dry eye sends out floods of watery tears.
Signs it might be MGD
- Gritty, burning or tired eyes that get worse through the day, and on screens or in the car
- Red or thickened lid edges, sometimes with small blood vessels along the rim
- Vision that smears, then clears when you blink
- Eyes that water outdoors, in wind or cold
- Styes or lid lumps that keep coming back
- Drops that help, but only for half an hour
None of these proves it on its own. The only way to know for sure is to look at the glands, ideally with an infrared photograph.
MGD is the most common cause of dry eye. In one large clinic study, 86% of people with dry eye had signs of it. It often travels with inflamed lid edges (blepharitis), and with rosacea, which inflames the small blood vessels along the lids.
Why oil-based drops suit MGD better than watery ones
Most people with dry eye reach for a watery drop first. For MGD that is a bit like topping up a bath with the plug out: the water you add evaporates just as fast as your own tears did, because the oil seal is still missing. You feel better for a few minutes, then you are back where you started.
A drop that adds back the oily part of the tear film, or slows evaporation, deals with the actual gap. In studies of evaporative dry eye, oil-based drops and drops that slow evaporation have generally done better on symptoms and tear stability than plain watery drops, though results vary from person to person. For a wider look at every kind of drop on a pharmacy shelf, see which eye drops suit which dry eye.
The drops and sprays that help MGD
Look at the ingredients on the box rather than the brand. These are the main options in UK pharmacies:
| Type | How it works | Good to know |
|---|---|---|
| Lipid emulsion drops | Milky-looking drops with oils such as mineral or castor oil that spread over the tear film | Can blur for a minute after use. Often the best first try |
| Liposomal sprays | A fine spray of tiny fat bubbles onto closed lids, which drifts onto the lid edge as you blink | No drops in the eye, handy if you find drops hard. Evidence is more mixed |
| Perfluorohexyloctane drops | A clear liquid that forms a layer over the tears and slows evaporation | Studied in large trials in people with MGD-related dry eye. Tiny drops, no preservative |
| Gels and ointments at night | Thicker lubricants that protect the eye while you sleep | Useful if your eyes are worst on waking. Blur, so bedtime only |
Try one type for two to three weeks, used regularly, before you judge it. Many people end up with an oil-based drop by day and a gel at night. If you wear contact lenses, check the box: most oil-based drops are meant to go in before the lenses or after they come out.
How to get the most out of them
Drops work far better as part of a daily routine than on their own. This is the order that makes sense:
- Warmth, about ten minutes. A heated eye mask on closed eyes softens the thickened oil. Use a mask rather than a flannel, which cools within about a minute. See how to do a warm compress properly.
- Gentle massage. Roll a clean fingertip along the lids towards the lashes, to ease the softened oil out.
- Clean the lid edges. A lid wipe or cleanser along the lash line, twice a day. Our home lid routine shows how.
- Then your drop or spray, through the day as you need it, and a gel at night if mornings are bad.
Small changes help the drops last: blink fully and look away from screens every 20 minutes, keep fans and car heaters off your face, and take make-up off every night. Use preservative-free products if you use drops more than four times a day.
Still gritty, even with the right drop?
Every treatment starts with a free consultation with one of our optometrists, in person or on the phone. We talk through what you have tried, whether your glands are likely blocked, and if treatment isn’t right for you, we say so before anything starts.
Why I don’t stop at drops
I have dry eye myself. It is the reason I stopped wearing contact lenses, and the reason laser eye surgery was never an option for me.
Drops have their place, and I use them. But when I set up the dry eye clinics at our five practices, the point was to look at the glands themselves, because a drop can’t tell you whether yours are blocked, shrinking or already gone.
What drops can’t do
A drop replaces some of the oil for as long as it lasts. It does not open a blocked gland, and it does not calm the inflamed lid edge that keeps re-blocking it. That matters, because a gland that stays blocked for long enough shrinks, and a gland that has gone does not come back.

That is not a reason to panic. Many people with mild MGD do well for years on warmth, lid care and a good drop. It is the reason not to rely on drops alone if they aren’t keeping you comfortable. For what the outlook usually looks like, see does dry eye go away?
What clears the glands
When home care isn’t enough, the glands can be treated directly. An optometrist can:
- Warm the glands with controlled heat, then press each one clear under magnification while the oil is soft, so you see what comes out.
- Clean the lid edge with a medical micro-brush, which removes the crusts and debris that block the openings. See lid cleaning in clinic.
- Calm the inflammation that keeps re-blocking the glands, with IPL (intense pulsed light) on the skin below the eyes and red light therapy, which calms inflammation, helps the glands regenerate and warms them slightly. See IPL and red light therapy.
How it all fits together, and what a course looks like, is on our MGD treatment page. If tiny mites at the lash roots are part of the problem, they need their own treatment: see eyelash mites (Demodex).
From your GP
For MGD with a lot of inflammation, or with rosacea, a GP may prescribe a course of antibiotic tablets at a low dose for some weeks, which calms the glands as much as it fights bacteria. We don’t prescribe ourselves, but we can write to your GP with what we have found.
Supplements
Omega-3 fish oil is often suggested. The largest trial so far found it did no better than an olive oil dummy capsule for dry eye, so we don’t tell people they need it. If you already take it and like it, there is no harm.
When to get help, and when you don’t need us
Get seen the same day if you have:
- A painful eye, rather than sore lid edges
- Vision that has dropped and doesn’t clear when you blink
- Strong light sensitivity, or one very red eye
- A red, painful eye while wearing contact lenses
Call any of our practices for an urgent appointment, or NHS 111. If it is severe and you can’t reach anyone, go to A&E. More in our list of urgent eye signs.
When you don’t need us: if warmth, lid care and a drop a few times a day keep you comfortable, keep going. That is good MGD care.
When it is worth coming in: if you still need drops many times a day after three or four weeks of a proper routine, if your lid edges stay red, if you keep getting styes, or if your eyes are getting worse year on year. Every treatment and its price is on our dry eye clinic page.
Questions people ask
What are the best eye drops for MGD?
Drops that add oil to the tears or slow evaporation usually suit MGD best: lipid emulsion drops, liposomal sprays or perfluorohexyloctane drops, preservative-free. Use them with warmth and lid cleaning, not instead of them.
Can eye drops unblock meibomian glands?
No. Drops stand in for the missing oil while they last. Warmth and massage at home can soften and move thickened oil, and blocked glands can be cleared by hand in clinic.
Does MGD go away on its own?
Mild MGD can settle with good home care, but it tends to come back if the routine stops. Glands that have shrunk do not grow back, so it is worth keeping on top of it.
How long until MGD drops work?
Many people feel some relief within minutes of each drop. Judge a new type over two to three weeks of regular use, alongside warmth and lid cleaning.
Are MGD drops available on the NHS?
For mild dry eye the NHS expects most people to buy lubricants from a pharmacy. A GP may prescribe for more severe cases, and can prescribe antibiotic tablets when inflamed lids are part of it.
- MGD means the oil glands in your lids are blocked, so your tears evaporate
- Oil-based drops, liposomal sprays and perfluorohexyloctane suit MGD better than watery drops
- Use them with warmth on the lids and lid cleaning twice a day
- Drops don’t unblock glands, and a gland that has gone doesn’t come back
- If you still need drops all day after a few weeks, the glands usually need clearing
Want to see your own glands?
Most people start with EyeRelief, and it starts with a free consultation, at any of our five practices: Cheadle, Heald Green, Middleton, Winsford and Heckmondwike. No referral needed.
- Nichols KK et al. The International Workshop on Meibomian Gland Dysfunction: executive summary. Investigative Ophthalmology & Visual Science, 2011.
- Jones L et al. TFOS DEWS II Management and Therapy Report. The Ocular Surface, 2017.
- Lemp MA et al. Distribution of aqueous-deficient and evaporative dry eye in a clinic-based patient cohort. Cornea, 2012.
- Tauber J et al. A phase 3 trial of perfluorohexyloctane for dry eye disease associated with meibomian gland dysfunction (GOBI). Ophthalmology, 2023.
- Dry Eye Assessment and Management (DREAM) Study Research Group. n−3 fatty acid supplementation for the treatment of dry eye disease. New England Journal of Medicine, 2018.